
Clinical case · Nerve injury · Rehabilitation
A documented clinical course following a severe traumatic injury of the common peroneal nerve: from early voluntary activation in October 2021 to electrophysiological signs of reinnervation and progressively more demanding rehabilitation activities through April 2022.
Severe traumatic injury of the common peroneal nerve
The injury occurred during a football match on 23 December 2020, following a severe hyperextension and valgus trauma of the right knee. Immediately after the injury, the player was unable to dorsiflex the right foot and developed sensory loss over the distal lower leg and foot, consistent with a complete motor palsy of the common peroneal nerve.
Emergency surgery was performed on 25 December 2020. Intraoperatively, the common peroneal nerve was found to be haemorrhagic, severely stretched and reduced to approximately half of its normal diameter over a segment of at least 4 cm. Importantly, the nerve remained anatomically continuous.
The nerve was surgically released through an extensive neurolysis, extending from approximately 10 cm above the fibular head to its division into the superficial and deep peroneal branches. The associated complete avulsion of the biceps femoris and lateral collateral ligament complex was anatomically repaired, restoring lateral knee stability and eliminating the excessive hyperextension that had placed additional tension on the nerve.

Beginning of regenerative treatment
Despite an extended period allowed for spontaneous recovery and previous therapeutic interventions, no improvement in motor function or ENMG findings had been observed in the clinical history available at the start of treatment. Targeted treatment under my supervision began in October 2021, almost ten months after the original injury.
Multimodal treatment programme
Treatment combined regenerative injection therapy, physiotherapy and individually tailored supplementation. Ultrasound-guided regenerative injections were administered in the region of the injured nerve segment, as well as in areas proximal and distal to the lesion.
After each treatment session, cutaneous sensation was reassessed to document changes in the extent of sensory loss and the areas in which sensation was returning.
The initial treatment schedule consisted of two sessions per day over a 15-day period, followed by a break of approximately four weeks from the intensive treatment programme. A total of three treatment cycles were completed.
Individually prescribed supplementation, electrotherapy and exercise-based physiotherapy were integrated into the treatment programme. Exercises and rehabilitation between treatment sessions were carried out in Zurich, in collaboration with Simon Hummer, an orthopaedic physiotherapist (@humsi_89 on Instagram).
Early clinical response
The initial clinical response was excellent. After the first treatments, the patient was able to produce a very small voluntary movement, visible as tension in the tendons at the front of the ankle. This had not been possible before treatment.
Motor function progressed the following day, with more pronounced visible tendon tension during attempted movement. During the treatment period, the area of cutaneous sensory numbness also decreased significantly. The sensory change was a clinical observation; it is not demonstrated by the videos.
VIDEO 1 · 14 October 2021
Early voluntary activation
VIDEO 2 · 15 October 2021
Activation the following day
Continued rehabilitation: November 2021
The November recordings document two complementary aspects of rehabilitation: single-leg balance and coordinated lower-limb control, and close-up follow-up of the foot and ankle during attempted movement.
These functional observations form part of the clinical record. The single-leg exercise is not an isolated test of common peroneal nerve function.
VIDEO 3 · 15 November 2021
Single-leg balance and control
VIDEO 4 · 23 November 2021
Foot and ankle activation
From local activation to walking and light running
Recordings from 5 and 6 January 2022 document close-up assessment of the foot and ankle, unassisted barefoot walking and light indoor running with changes of direction. Together, they show the functional activities the patient was performing before the follow-up ENMG examination.
VIDEO 5 · 5 January 2022
Close-up movement assessment
VIDEO 6 · 5 January 2022
Barefoot walking
VIDEO 7 · 6 January 2022
Progression to light running
Follow-up ENMG: evidence of ongoing reinnervation
At the follow-up ENMG examination on 20 January 2022, voluntary dorsiflexion of the foot and toes was returning. Voluntary contraction of the tibialis anterior and toe extensors was documented, and the patient could hold the foot against gravity. The lateral peroneal muscles were graded M2/5.

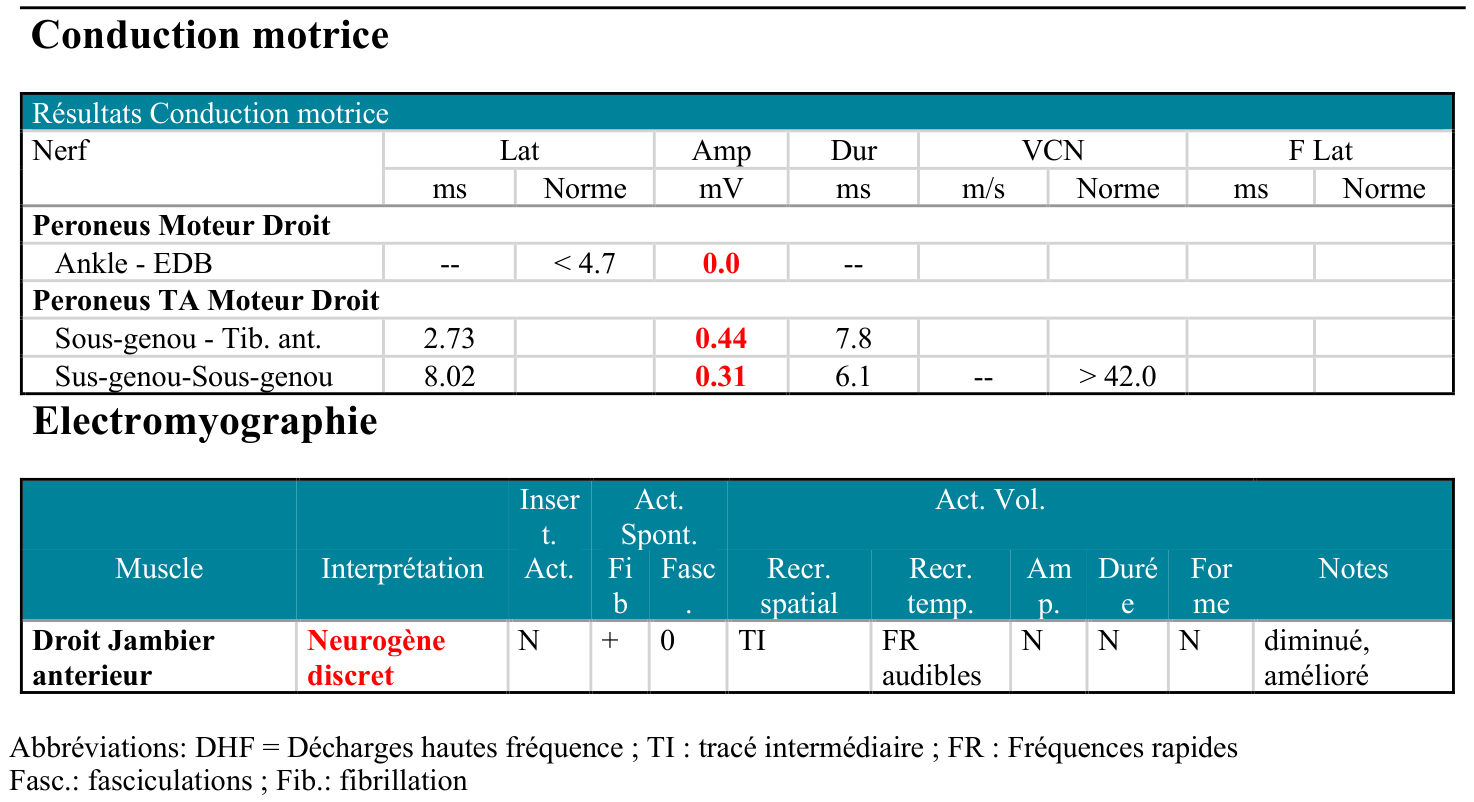
The distal motor response recorded from the extensor digitorum brevis remained absent (0.0 mV), while low-amplitude responses were recorded from the tibialis anterior (0.44 mV with below-knee stimulation and 0.31 mV with above-knee stimulation). The examiner did not find improved absolute motor neurography values compared with November 2021 and noted possible technical interference, including co-stimulation and local swelling.
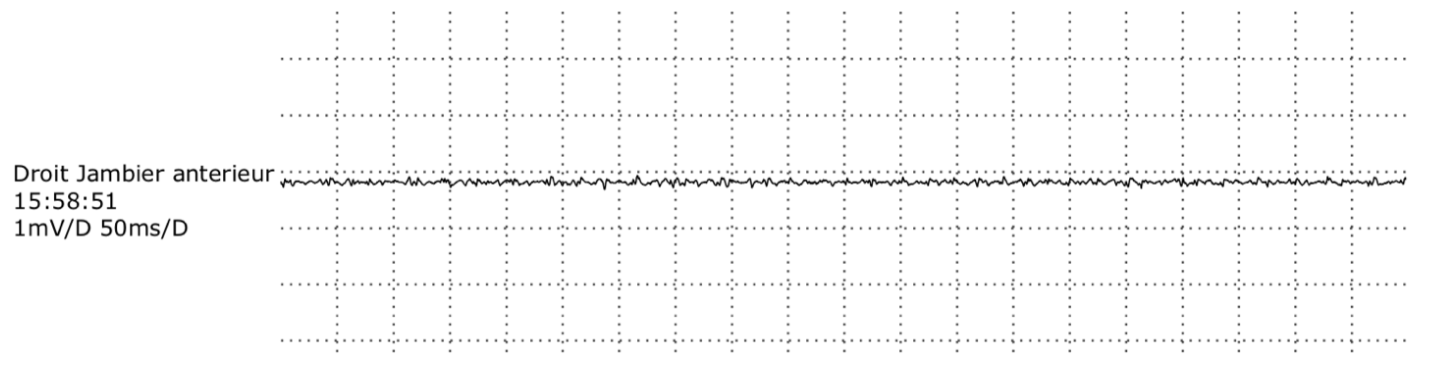
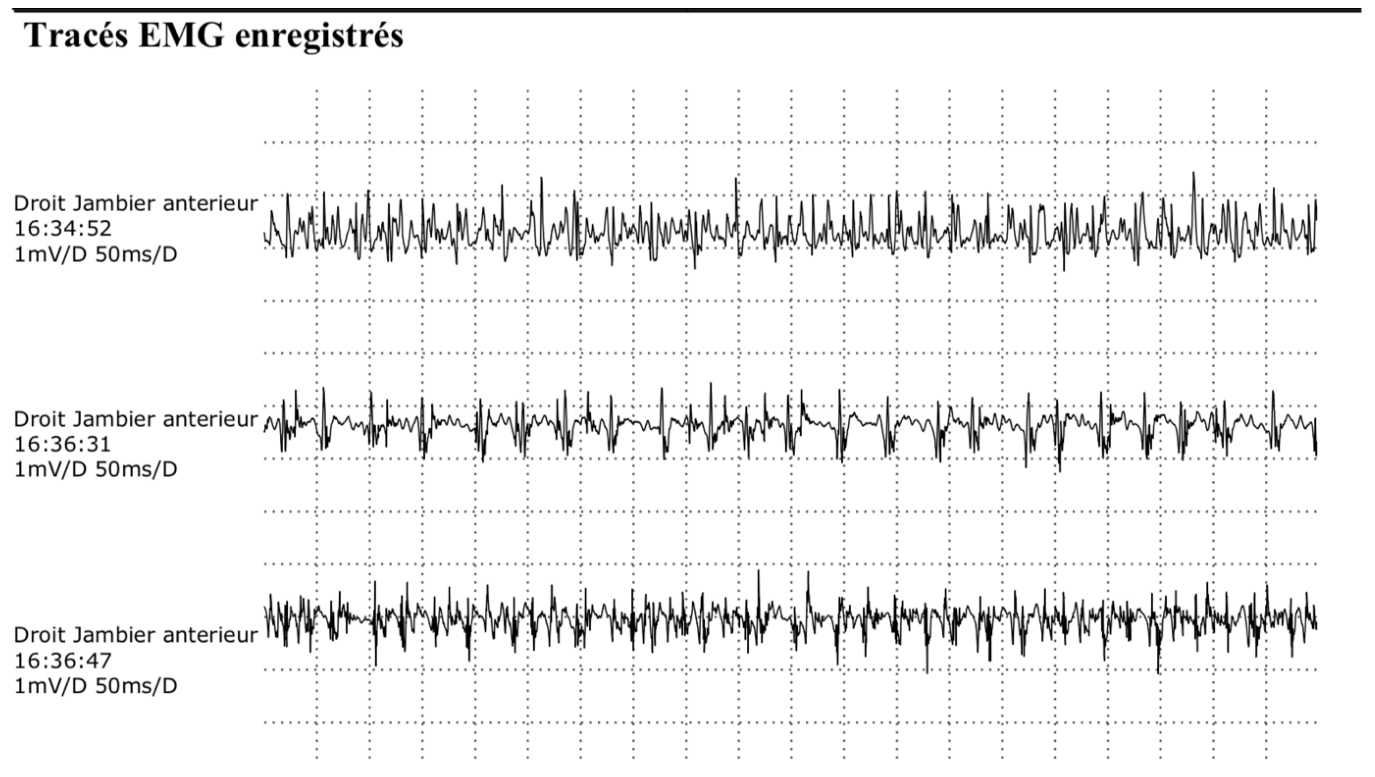
Needle EMG nevertheless showed less spontaneous activity at rest than in November 2021, together with recruitment of motor units of improved size. Remodelled motor units were present alongside units of normal morphology and slightly below-normal size. The examiner interpreted these findings as evidence of renewed muscular activity through reinnervation, involving collateral sprouting and probably terminal axonal regrowth.
The positive follow-up findings were renewed voluntary muscle activity and needle-EMG signs of ongoing reinnervation. Recovery remained incomplete, and absolute motor neurography values had not improved.

View the motor neurography and needle-EMG measurements
EMG recordings: November 2021 and January 2022
The follow-up report includes the earlier comparison tracing and the later tibialis anterior recordings. The November examination took place after treatment had begun in October, so this is a comparison during treatment rather than a pre-treatment baseline.
Further functional progression: February–April 2022
The later recordings extend the clinical documentation beyond the January ENMG. On 22 February 2022, the patient was recorded running on a football pitch, turning and returning. By 17 March 2022, the footage documents repeated single-leg hopping and balance adjustments during landing. The recording from 12 April 2022 shows low-hurdle jumps followed by acceleration into running.
VIDEO 8 · 22 February 2022
On-field running
VIDEO 9 · 17 March 2022
Single-leg hopping and landing
VIDEO 10 · 12 April 2022
Hurdle jumps and acceleration
These recordings document progression to increasingly demanding rehabilitation activities. They do not, by themselves, establish complete neurological recovery or readiness for unrestricted competitive football.
Clinical perspective
This case brings together the operative description of a severe nerve-stretch injury with preserved continuity, the early clinical response observed after targeted treatment began in October 2021, independent electrophysiological evidence of ongoing reinnervation in January 2022, and subsequent video documentation of functional rehabilitation through April 2022.
The recordings and ENMG findings describe different aspects of recovery. The early changes were clinical observations, while the later ENMG documented reinnervation. This individual clinical course records improvement during treatment and rehabilitation; it does not isolate the contribution of any one intervention from the wider recovery process.
Clinical documentation: operative report dated 25 December 2020; follow-up ENMG dated 20 January 2022, including a comparison with November 2021; treating physician’s clinical observations; and ten video recordings dated October 2021–April 2022. Report excerpts retain their original language and measurements, with direct patient identifiers excluded. Video dates follow the supplied file labels.